Picture a Monday morning. Eleven people are queuing, the phone is ringing, and a patient is spelling out her new surname while the receptionist types with one hand. That thirty-second exchange will shape healthcare data quality for years, because whatever lands in the system tends to stay there.
Most practices don’t have a data problem so much as a thousand small, tolerated habits. A missing allergy field here, a mobile number with a digit out of place there. None of it feels urgent until a claim bounces, a recall letter goes to the wrong address, or a clinician can’t trust what’s on screen.
This article gives you seven practical ways to tighten things up. They are woven through the sections below, and you can work through them in any order. Start with the one that irritates your team most, because that’s usually where the damage is.
The first step is simply to look. Run a practice data audit on a sample of 100 records and count how many have a missing or doubtful field. Your own number will motivate more than any statistic I could quote. Repeat it quarterly, because a single audit tells you where you stand but not which way you’re moving. Industry guidance on risk work, including HealthIT.gov’s privacy and security resources for providers, makes the same point about regular review rather than a once-off exercise.
Patient Data Accuracy: Get the Basics Right at Registration
Patient data accuracy is won or lost in the first two minutes of a relationship. Names, dates of birth, contact numbers, medical aid or insurance details and next of kin are the fields everything else hangs off. If any of them is wrong, every downstream process inherits the error.
Make verification a habit, not an event. Ask patients to confirm their details on arrival, out loud or on a tablet, and not only when something has visibly changed. A quick “is this still your best mobile number?” catches more problems than any clean-up project, and it takes five seconds.
Duplicate patient records deserve their own mention. They appear when someone is registered as “Mike” on one visit and “Michael” on the next, or when a married name replaces a maiden name. The result is a split history: allergies on one file, test results on another. Search by several identifiers before creating a new file, and schedule a monthly merge review so duplicates never pile up.
Standardise how things are written, too. Agree on date formats, how to record double-barrelled surnames, and whether you store titles. It sounds fussy, but consistent conventions are what make search, reporting and clean patient records possible at all.
Medical Records Completeness: Closing the Gaps Clinicians Leave Behind
A record can be perfectly accurate and still useless if half of it is empty. Medical records completeness is about whether the next clinician, or you in two years, can reconstruct what happened and why. The Medical Protection Society’s record keeping tips are a good reminder that notes should be contemporaneous, clear and sufficient to justify decisions.
Doctors don’t skip fields out of laziness. They skip them because the screen asks for too much, in the wrong order, in the middle of a consultation. One large study of workflow redesign reported by the American Medical Association described organisations that cut clicks, shared templates and trimmed alerts, freeing up meaningful time each day. Less friction means more complete notes.
So ask your clinicians what slows them down, then fix that. Build templates around your most common presentations, make mandatory only the fields you genuinely need, and move the rarely used ones out of the way. Diagnosis coding matters here as well. The World Health Organization’s ICD classification underpins coding systems used around the world, and national variants such as the CDC’s ICD-10-CM in the United States run to tens of thousands of codes. Vague or outdated codes slow reimbursement, so build a habit of checking that the code matches the note.
Finally, set a rule for how quickly notes must be finished. Same day is ideal. Anything left until Friday afternoon is a note written from memory.
Data Entry Errors in Healthcare: Where They Hide and How to Catch Them
Data entry errors in healthcare rarely look dramatic. They look like a transposed digit in a policy number, a free-text “penicillin?” in the allergy box, or a procedure code picked from the wrong line of a dropdown. Small things, with a long tail.
The most expensive place to find them is at the claims stage. A rejected claim means someone has to investigate, correct and resubmit, and the cash arrives weeks later. Medical Economics’ practical billing workflow tips stress catching problems before submission, which is exactly right. Check eligibility and mandatory fields at booking, not at billing.
Validation rules do a lot of quiet work. Required fields, format checks on phone numbers and ID numbers, and drop-down lists instead of free text all stop errors at the point of entry. Track your rejection reasons for a month and you’ll usually find that three or four causes account for most of the pain. Fix those first.
Measure what you fix. The MGMA’s guidance on practice financial metrics is a useful starting point for choosing indicators such as denial rate and days in accounts receivable. When those numbers move, you can trace the improvement back to cleaner data.
Protecting What You’ve Cleaned: Security, Access and Training
Clean data that anyone can edit won’t stay clean. Limit who can change demographic and clinical fields, keep an audit trail of changes, and review access whenever staff join or leave. Both Medical Economics’ cybersecurity steps and its advice on data security point to the same basics: multifactor authentication, encryption, software updates and tested backups.
Human error sits behind a large share of breaches, so training is not optional. A short refresher twice a year, with real examples from your own practice, works better than an annual slideshow. Remember too that privacy law varies by country, so check what your own regulator requires rather than assuming a single rule applies everywhere.
Where GoodX Fits Into Your Data Quality Routine
Good habits need good tools behind them. GoodX practice management software brings bookings, clinical records, billing and reporting into one system, so a patient’s details are captured once and reused everywhere instead of retyped in three places. Fewer re-entries means fewer chances for errors to creep in.
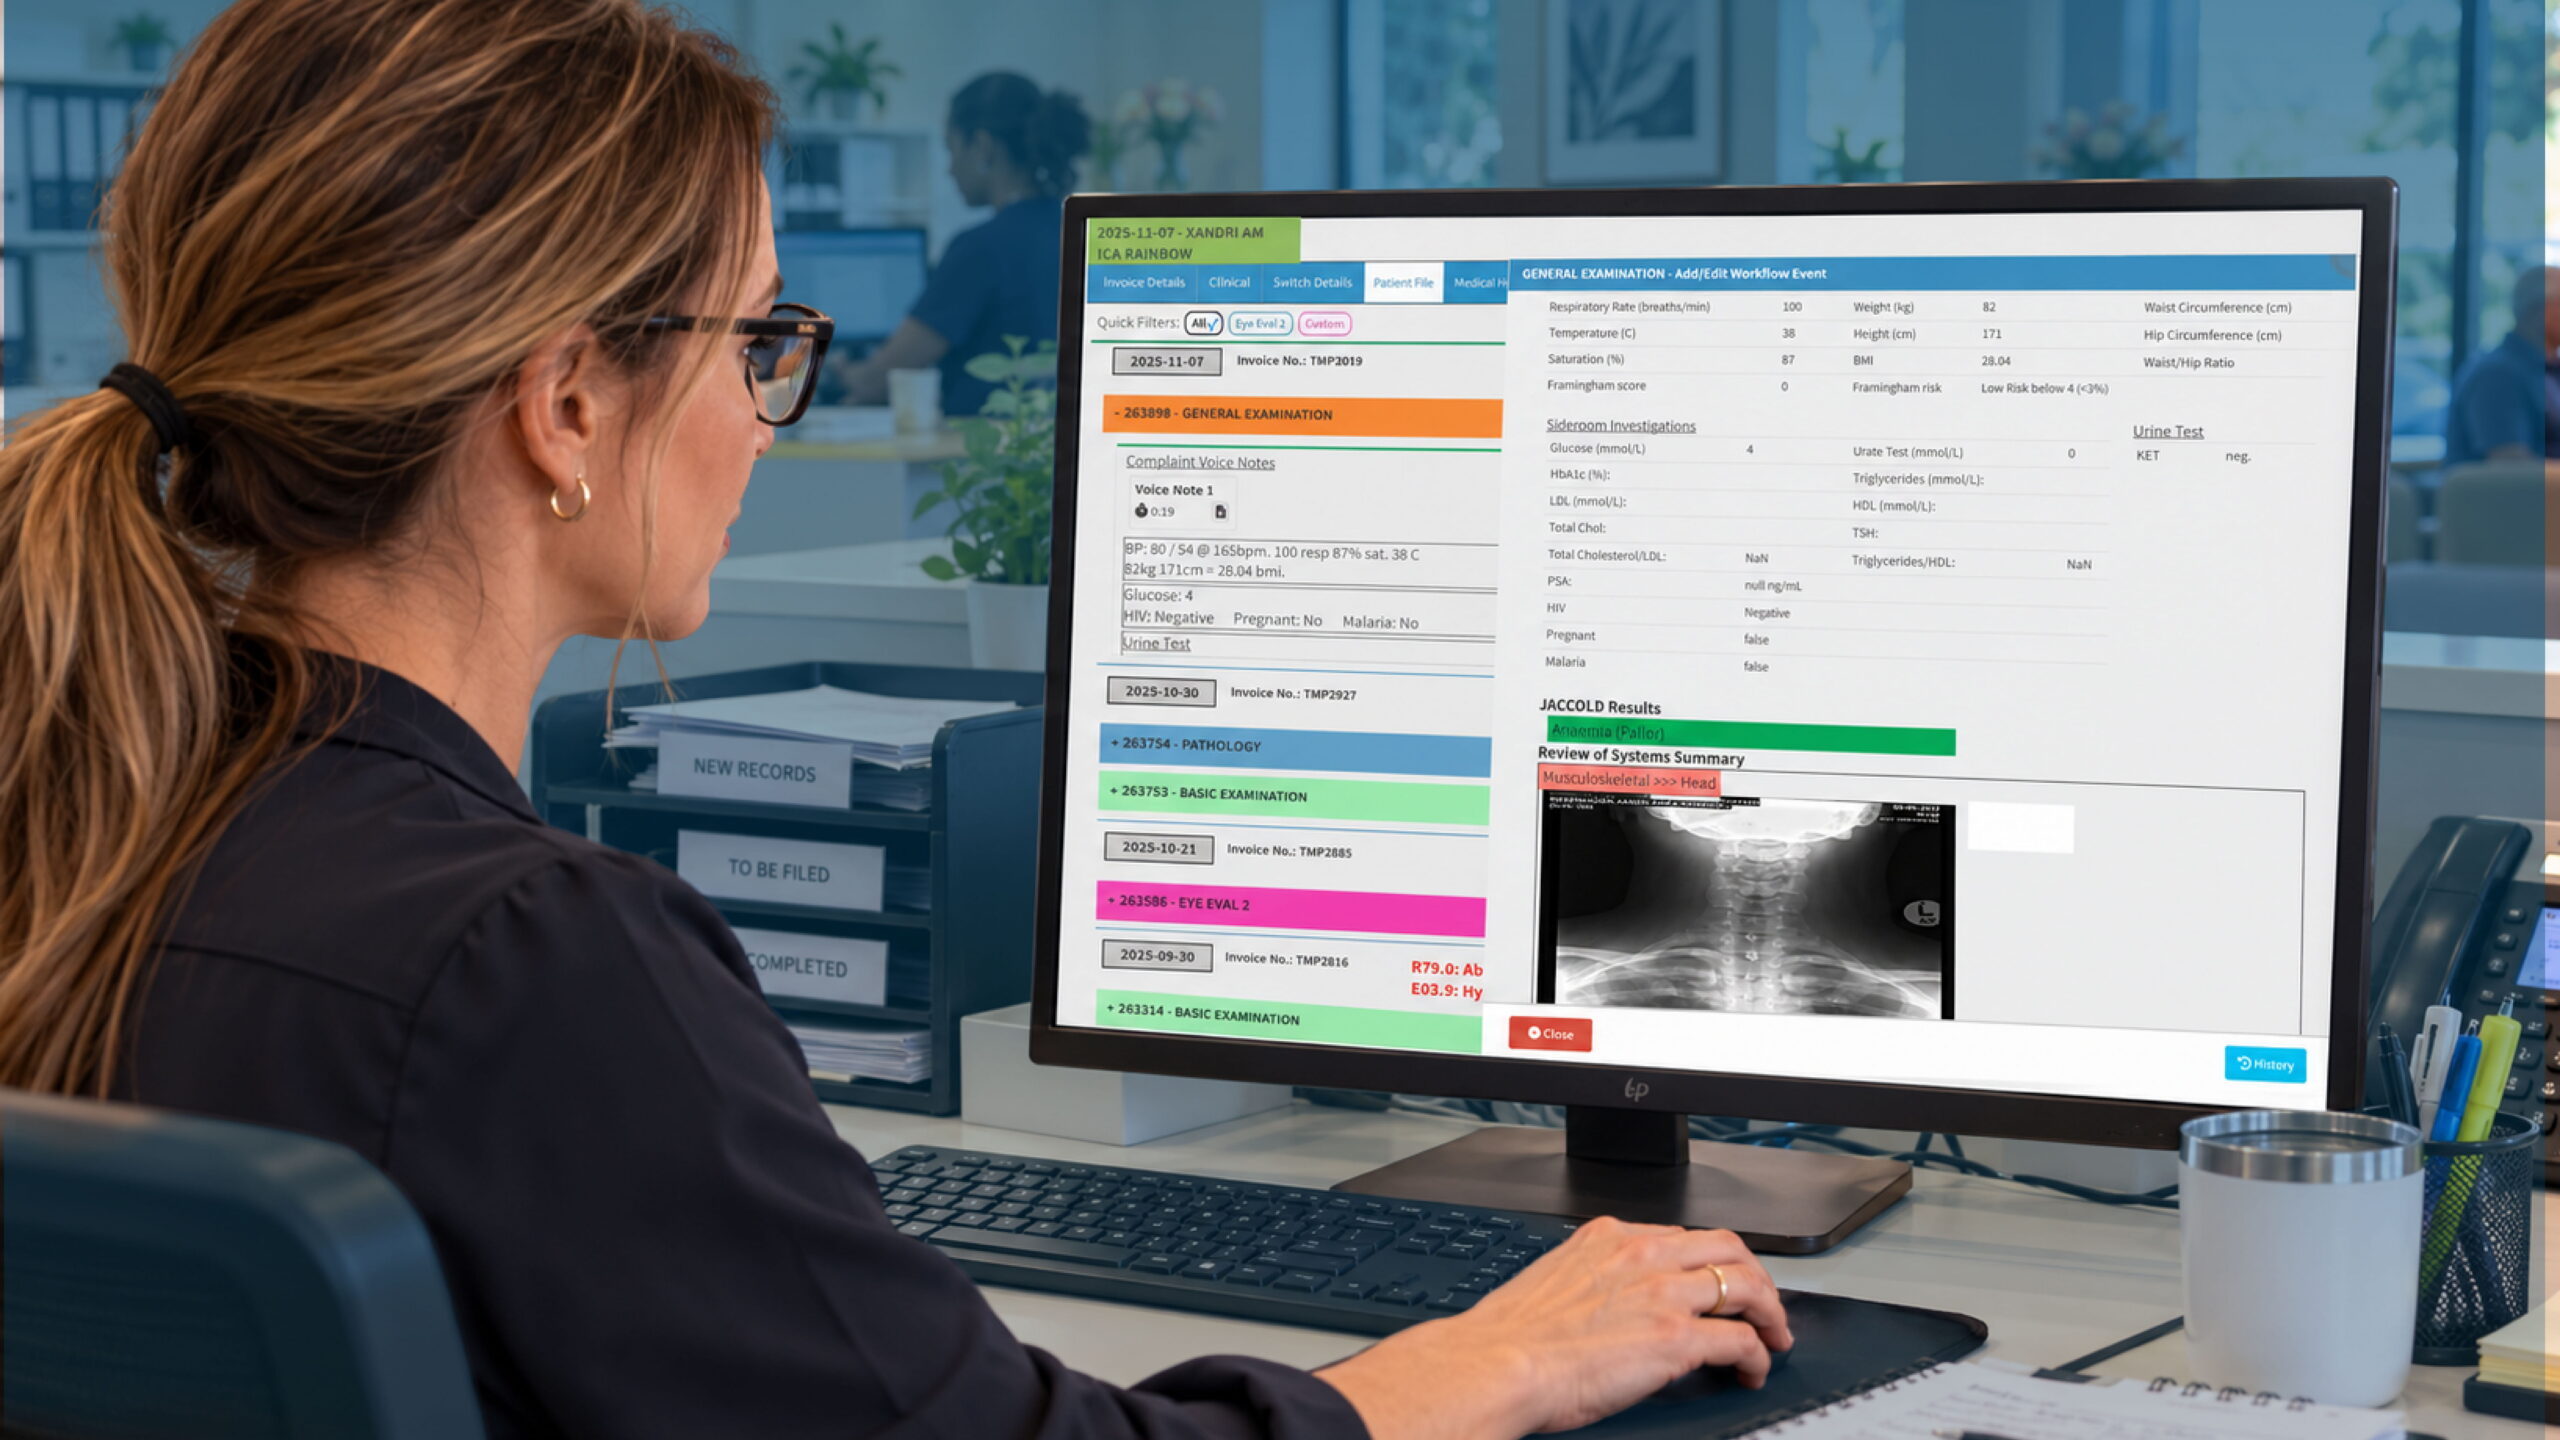
Practically, that helps in several ways. Structured clinical records and templates support completeness, automation takes repetitive admin off busy staff, and reporting makes it easier to spot gaps and rejection patterns during a practice data audit. Billing and claims workflows benefit directly when the underlying registration data is right. You can explore how [INTERNAL LINK: GoodX clinical records and billing tools -> GoodX features page] fit together for a small team.
Software won’t carry your compliance duties for you, and any honest vendor will say so. What it can do is make the right way the easy way, which is most of the battle. For a wider view of how national systems approach this, the WHO’s work on digital health offers useful context.
If you want a place to begin, read our guide on [INTERNAL LINK: running a practice data audit -> GoodX blog on practice audits] and pair it with your next team meeting.
Frequently Asked Questions
What is healthcare data quality?
Healthcare data quality is the degree to which patient and practice information is accurate, complete, consistent and timely. High-quality data lets clinicians trust what they see, supports correct billing, and makes reporting reliable. Poor quality shows up as rejected claims, duplicate files and gaps in clinical notes.
How often should a practice run a data audit?
Quarterly is a sensible rhythm for most practices. Review a sample of around 100 records, count missing or doubtful fields, and track the trend over time. Smaller, more frequent checks, such as a monthly duplicate review, keep problems from building up between audits.
What causes duplicate patient records?
Duplicates usually come from name variations, changed surnames, typing mistakes and registering someone without searching properly first. Searching on several identifiers before creating a file prevents most of them. Regular merge reviews clean up the rest before clinical history becomes fragmented.
How do data entry errors affect billing?
Data entry errors lead to rejected or delayed claims, because insurers and schemes check details such as member numbers, codes and patient identifiers. Each rejection costs staff time and slows cash flow. Validating information at booking and before submission prevents most avoidable denials.
Can software fix data quality on its own?
No, software supports good data quality but can’t replace good habits. Validation rules, templates and shared records reduce errors, yet staff training, clear procedures and regular audits are still needed. Think of software as the foundation and your team’s routines as the structure built on it.
Book your free GoodX demo
Want to see how cleaner records and fewer rejected claims could work in your own practice? Book a free demo and we’ll walk you through the tools with your workflow in mind. Start at goodx.international.
Disclaimer: This article is provided for general informational and educational purposes only. While GoodX Software takes reasonable care to ensure that the information is accurate and current at the time of publication, laws, regulations, industry standards, healthcare policies and technology may change. The content should not be regarded as medical, legal, financial or other professional advice. Readers should verify information relevant to their circumstances and consult an appropriately qualified professional where necessary. GoodX Software accepts no responsibility for decisions made or actions taken solely on the basis of this content.